The abdominal plates
Boston Peptide: tesamorelin laboratory research
The abdominal studies distinguish fat around organs from fat within the liver. Their approved medical setting is HIV-associated lipodystrophy.
What peptide is TSM?
If “TSM peptide” or “tesmoralin” brought you here, the compound covered below is tesamorelin. It is a synthetic analogue of growth hormone-releasing hormone, the signal that prompts the pituitary gland below the brain to release growth hormone. Tesamorelin increases the body’s own hormone pulses.
The LiverTox monograph describes its approved use for excess abdominal fat in adults with HIV-associated lipodystrophy. This condition involves abnormal fat distribution. General weight loss, anti-ageing and changing a healthy person’s physique have a much weaker evidence base than that specific medical use.
Fat compartments
Stanley and colleagues studied 50 adults with HIV and abdominal fat accumulation who were receiving antiretroviral therapy. Random assignment placed 28 in the tesamorelin group and 22 in the placebo group. The study lasted 6 months.
The treatment effect on visceral fat was −42 cm². Hepatic lipid-to-water percentage also decreased, with a net change of −2.9%. Visceral means around the internal organs; hepatic means within the liver in this measurement. The units preserve the distinction: an area of abdominal fat and a liver composition measure.
Pulling the abdomen apart like this suits my curiosity. The same abdomen contains separate places to measure change, and a result at one location leaves another question to investigate. Those anatomical distinctions sharpen my interest; “fat burning” leaves me with almost nothing to picture.
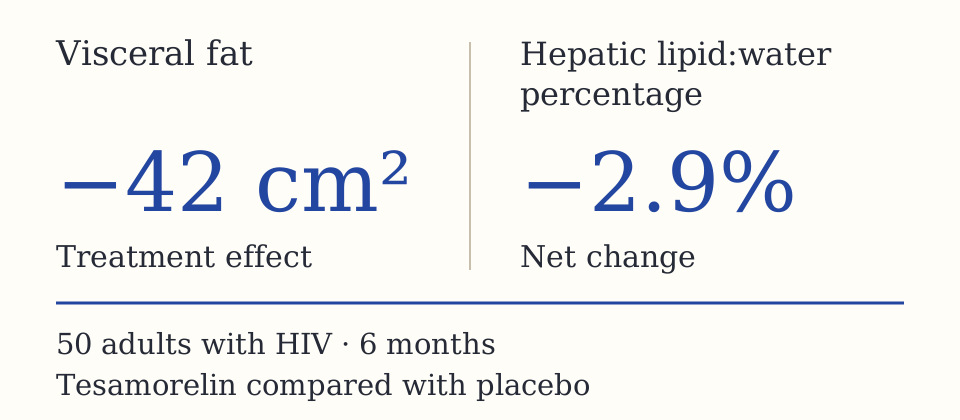
Hormone pulses
The short mechanistic study in 13 healthy men examined a different question. Over 2 weeks, tesamorelin increased mean overnight growth hormone and IGF-1, insulin-like growth factor 1, a protein involved in cell growth. Fasting glucose and insulin-stimulated glucose uptake showed no statistically significant change during that study.
The hormone response helps explain the drug’s action. Growth hormone encourages the use of stored fat, and the liver produces more IGF-1 in response. Increasing these signals raises a further question about unwanted growth and long-term safety. The short glucose result gives a limited observation in healthy men; its duration cannot settle later glucose effects.
The pulse has its own fascination for me. Tesamorelin stimulates release from the pituitary, whereas supplying growth hormone directly would enter the system at a different point.
Five trials together
A 2026 meta-analysis combined five randomized trials in HIV-associated lipodystrophy. It reported pooled mean differences of −27.71 cm² in visceral fat, −1.18 kg in trunk fat and −4.28% in hepatic fat fraction, with +1.42 kg in lean body mass.
Trunk fat includes the fat around abdominal organs. Lean mass contains muscle and water, so the increase cannot all be assigned to new muscle. The review gathers several body-composition observations into one place, while its participants remain adults with the HIV-associated condition.
Treating that pattern as permission to replace one fat-loss drug with another stretches my confidence. Semaglutide acts through GLP-1 and has its own trial populations and outcomes. The relevant comparison begins with the medical problem being treated.
After stopping
The 52-week tesamorelin programme reported a sustained visceral-fat reduction of −18% from baseline during continued treatment. Visceral fat reaccumulated after treatment stopped. Glucose-parameter changes over the programme were not clinically significant.
The return of the fat changes the appeal of a permanent-remodelling story. What the study demonstrates is a reduction maintained during treatment, with reversal after discontinuation. The duration and the stopping observation deserve equal billing with the initial decrease.
Growth signals and safety
Tesamorelin raises IGF-1, so unwanted cell growth and long-term cancer risk remain important concerns. Active malignancy is a labelled contraindication. Growth-hormone stimulation can also weaken insulin’s action; short or selected trials with reassuring average glucose findings leave individual and longer-term risks unresolved.
LiverTox judges clinically apparent liver injury from tesamorelin unlikely. That is reassuring about a particular kind of harm. It leaves the growth-factor and blood-sugar questions to be considered separately.
The drug remains a prescription treatment for its specific HIV-associated fat indication. Material supplied for laboratory research lacks the identity, purity and potency oversight of the approved medicine. Tesamorelin is also prohibited in competitive sport under growth-related rules, a separate regulatory setting from medical approval.
The participants’ later health is the question nagging at me. The anatomical findings already justify attention; durable benefit and safety require their own answers.